From the free course Criminology and Criminal Justice on Lykke
Mental Health in the Justice System
Key concepts: Deinstitutionalization · Competency to Stand Trial · Mental Health Courts · Dual Diagnosis · Crisis Intervention
The history of mental health treatment and the challenges of managing mental disorders within the legal framework.
Mental Health in the Justice System
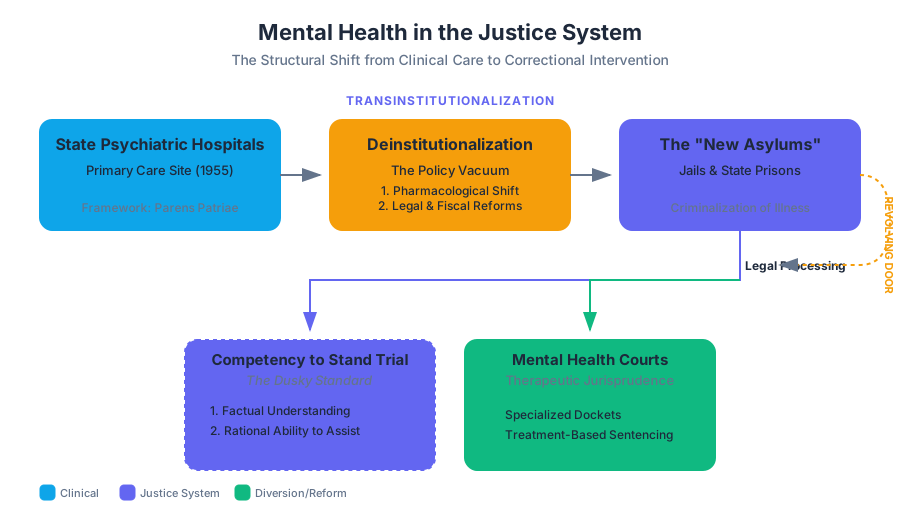
The intersection of mental health and the criminal justice system represents one of the most complex "wicked problems" in modern governance. Over the last half-century, the United States has undergone a structural shift where the primary locus of mental health care has migrated from clinical settings to correctional facilities. This phenomenon, often termed transinstitutionalization, has forced law enforcement, the judiciary, and corrections officers to become the de facto front-line providers of psychiatric intervention.
Deinstitutionalization and the "New Asylums"
Deinstitutionalization refers to the policy of moving severely mentally ill people out of large state institutions and then closing part or all of those institutions. While intended as a humanitarian reform to replace "warehousing" with community-based care, the failure to adequately fund community resources led to a vacuum.
What it is
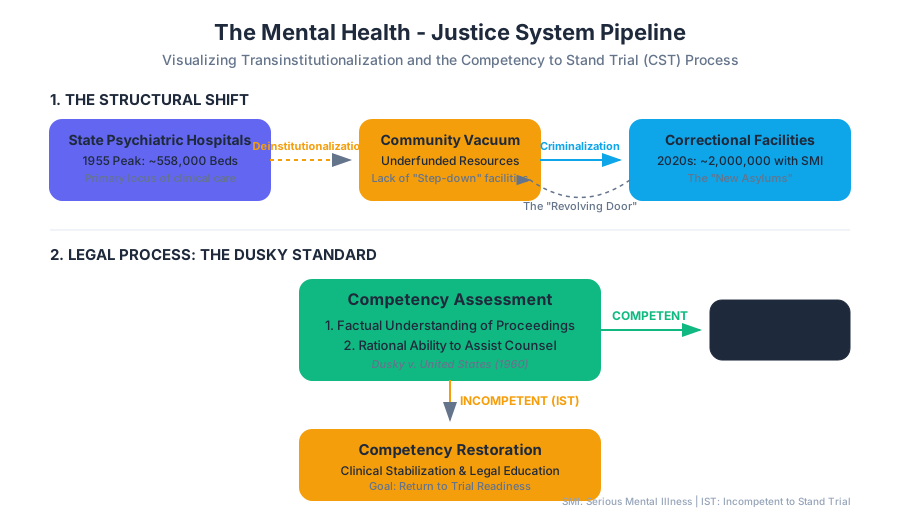
Historically, the United States relied on large, state-run psychiatric hospitals. In 1955, there were approximately 558,000 beds in state psychiatric hospitals; by 2016, that number plummeted to fewer than 38,000. This 93% reduction was driven by three primary factors:
- Pharmacological Advancements: The introduction of antipsychotics like chlorpromazine (Thorazine) in the 1950s.
- Legal Shifts: Supreme Court rulings (e.g., O'Connor v. Donaldson) that restricted the state's ability to confine non-dangerous individuals.
- Fiscal Policy: The creation of Medicaid and Medicare, which incentivized states to move patients out of state-funded hospitals and into community settings where federal matching funds were available.
Why it matters
The "Dark Figure of Crime" for the mentally ill is often a reflection of survival strategies. Without stable housing or treatment, many individuals with Serious Mental Illness (SMI) engage in "nuisance crimes" (vagrancy, public intoxication, trespassing). This has led to the Criminalization of Mental Illness, where the justice system is used to manage social problems that the healthcare system has failed to address.
| Metric | 1955 (Peak Institutionalization) | 2020s (Post-Deinstitutionalization) |
|---|---|---|
| Primary Care Site | State Psychiatric Hospitals | County Jails and State Prisons |
| Patient/Inmate Count | ~558,000 in hospitals | ~2,000,000 in jails/prisons (with SMI) |
| Legal Framework | Parens Patriae (State as Parent) | Due Process and Public Safety |
| Funding Source | State General Funds | Medicaid, Local Tax, Corrections Budgets |
Common Pitfalls
A common misconception is that deinstitutionalization caused mental illness. It did not; it changed the geography of mental illness. The "revolving door" phenomenon—where individuals are repeatedly arrested for minor offenses, released, and re-arrested—is a direct result of the lack of "step-down" facilities between the jail and the street.
Competency to Stand Trial (CST)
Competency to Stand Trial is a constitutional requirement rooted in the Due Process Clause of the 14th Amendment. It ensures that a defendant has the "sufficient present ability to consult with his lawyer with a reasonable degree of rational understanding."
How it works: The Dusky Standard
The landmark case Dusky v. United States (1960) established the two-pronged test for competency:
- Factual Understanding: Does the defendant understand the charges, the roles of the court participants (judge, jury, prosecutor), and the possible penalties?
- Rational Understanding: Can the defendant assist their counsel in their own defense?
"The test must be whether he has sufficient present ability to consult with his lawyer with a reasonable degree of rational understanding—and whether he has a rational as well as factual understanding of the proceedings against him." — Dusky v. United States
Implementation and Restoration
If a defendant is found Incompetent to Stand Trial (IST), the criminal proceedings are paused. The state then attempts Competency Restoration, usually through medication and legal education. If a defendant cannot be restored in a reasonable timeframe (Jackson v. Indiana), the state must either release them or initiate civil commitment proceedings.
Mental Health Courts (MHCs)
Mental Health Courts are specialized dockets that use a therapeutic jurisprudence model. Rather than focusing solely on punishment, these courts aim to address the underlying mental health issues that contribute to criminal behavior.
The Four Pillars of MHCs
- Voluntary Participation: Defendants must agree to participate, often in exchange for a suspended sentence or dismissed charges.
- Multidisciplinary Team: Includes a judge, prosecutor, defense counsel, and mental health clinicians.
- Judicial Supervision: Frequent status hearings where the judge interacts directly with the participant.
- Graduated Sanctions and Incentives: Positive reinforcement for compliance (e.g., reduced reporting) and therapeutic adjustments for non-compliance.
| Feature | Traditional Criminal Court | Mental Health Court |
|---|---|---|
| Goal | Adjudication and Punishment | Rehabilitation and Stability |
| Process | Adversarial | Collaborative |
| Outcome | Sentence (Jail/Probation) | Treatment Plan and Supervision |
| Judge's Role | Neutral Arbiter | "Coach" and Monitor |
| Success Metric | Recidivism (New Arrests) | Treatment Adherence and Quality of Life |
Dual Diagnosis (Comorbidity)
In the context of the justice system, Dual Diagnosis (or Co-occurring Disorders) refers to the presence of both a mental health disorder and a substance use disorder (SUD). This is the rule rather than the exception among justice-involved individuals.
Why it matters
Individuals with dual diagnoses are significantly more difficult to treat and have higher rates of recidivism. The "self-medication hypothesis" suggests that many individuals use illicit substances to manage the symptoms of untreated SMI (e.g., using stimulants to counter the lethargy of depression or alcohol to quiet auditory hallucinations).
The Feedback Loop
The interaction between SMI and SUD creates a "multiplier effect" on criminal risk:
- SMI impairs judgment and impulse control.
- SUD increases the likelihood of engaging in illegal markets and brings the individual into contact with law enforcement.
- Incarceration often interrupts treatment for both, leading to acute withdrawal and psychiatric crisis upon release.
Crisis Intervention Teams (CIT)
The Crisis Intervention Team (CIT) model, often called the "Memphis Model," is a police-based first responder program that has become the gold standard for law enforcement's handling of mental health crises.
How it works
CIT involves a specialized 40-hour training program for a subset of patrol officers. The training covers:
- Signs and Symptoms: Recognizing psychiatric disorders.
- De-escalation Techniques: Verbal strategies to lower the emotional temperature of an encounter.
- Lived Experience: Hearing from individuals who have experienced psychiatric crises.
- System Navigation: Understanding where to take an individual for help (Diversion Centers) rather than jail.
The De-escalation Pipeline
- Engagement: Approach with a non-threatening posture; use a calm voice.
- Assessment: Determine if the behavior is driven by psychosis, intoxication, or medical emergency (e.g., diabetic shock).
- Stabilization: Use active listening to validate the person's feelings without necessarily validating their delusions.
- Resolution: Direct the individual to a crisis center or hospital rather than a correctional facility.
The "Officer's Dilemma": Before CIT, officers often had only two choices when encountering a mentally ill person in crisis: "Arrest" or "Walk Away." CIT provides a third path: "Referral to Treatment."
Legal Defenses: Insanity vs. Competency
A frequent point of confusion in both public discourse and legal practice is the distinction between Competency and the Insanity Defense (Not Guilty by Reason of Insanity - NGRI).
Comparison of Legal Standards
| Dimension | Competency (CST) | Insanity (NGRI) |
|---|---|---|
| Timing | State of mind during the trial. | State of mind at the time of the crime. |
| Legal Basis | Due Process (14th Amendment). | Criminal Responsibility (Mens Rea). |
| Outcome of Finding | Postponement of trial; treatment. | Acquittal (usually followed by commitment). |
| Frequency | Very Common (thousands per year). | Very Rare (less than 1% of cases). |
| Burden of Proof | Usually the defense (preponderance). | Usually the defense (clear and convincing). |
Variations of the Insanity Defense
- M'Naghten Rule: Focuses on cognitive capacity—did the defendant know the "nature and quality" of the act or that it was wrong?
- Irresistible Impulse: Focuses on volitional capacity—could the defendant control their actions even if they knew they were wrong?
- Model Penal Code (MPC): A combination—did the defendant lack "substantial capacity" to appreciate the wrongfulness or conform their conduct to the law?
Common Pitfalls
The "Insanity Defense" is not a "get out of jail free" card. In reality, individuals found NGRI often spend more time confined in secure psychiatric hospitals than they would have spent in prison for the same offense.
Operational Challenges in Corrections
Once an individual with SMI is incarcerated, the challenges shift from the street to the cell block. Prisons are inherently anti-therapeutic environments: they are loud, brightly lit, crowded, and characterized by a rigid hierarchy.
The Solitary Confinement Paradox
Inmates with mental illness often struggle to follow complex prison rules. This leads to disciplinary infractions, which frequently result in Administrative Segregation (solitary confinement). However, solitary confinement is known to exacerbate psychiatric symptoms, leading to a "decompensation spiral."
Medication Management
Ensuring "continuity of care" is a massive logistical hurdle. When an individual is arrested, their community prescriptions are often not transferred.
- Formulary Restrictions: Jails may not carry the specific (and expensive) second-generation antipsychotics the inmate was taking.
- Refusal of Treatment: Inmates have a limited right to refuse medication (Washington v. Harper), unless they are a danger to themselves or others.
Future Directions: The Sequential Intercept Model (SIM)
The Sequential Intercept Model provides a framework for communities to organize their response to mental illness in the justice system. It identifies six "intercept" points where an individual can be diverted from the system into treatment.
- Intercept 0 (Community Services): Crisis lines, mobile crisis teams, and "warm lines."
- Intercept 1 (Law Enforcement): CIT training and co-responder models (police + clinicians).
- Intercept 2 (Initial Detention/Court): Jail screening and post-arrest diversion.
- Intercept 3 (Jails/Courts): Mental Health Courts and specialty dockets.
- Intercept 4 (Reentry): Transition planning from jail/prison back to the community.
- Intercept 5 (Community Corrections): Specialized probation and parole caseloads.
By visualizing the justice system as a series of filters, the SIM allows policymakers to identify where the "leaks" are—where individuals are falling through the cracks and into deeper levels of involvement.
Source Materials
- Introduction to the American Criminal Justice System (Burke et al.)
- Mental Disorders and the Criminal Justice System (Nichol)
- Chapter 2: Mental Disorders in the Criminal Justice System
- Chapter 7: Courts
- 5: Class, Race, Gender and Criminal Justice- Understanding Disparities in the System
- Save as PDF
- Save as PDF
- Save as PDF
Study Criminology and Criminal Justice on Lykke
This course page is free to open: signed out, you can read its first two sections, and signing in, on any plan, opens the rest. The free Lykke Chrome extension syncs your own Canvas courses, so ChatGPT, Claude and Muse can answer from your classes and deadlines. It only reads Canvas.
Add the free extensionSign in to open every sectionAll sections of Criminology and Criminal Justice · Browse more course pages